3M Bair Hugger temperature management solutions

Proven Evidence. Trusted Performance.
The most studied warming solution


The Bair Hugger warming system is backed by more published outcomes research.*"
*Compared to other leading convective and conductive warming systems on the market
Chosen by the best. Proven around the world.
The Original forced-air warming technology


Supported by extensive clinical evidence, trusted in practice, and helping clinicians make confident, data-informed decisions every day.

Solutions for every stage of care
Blankets, gowns and monitoring — designed with patients in mind
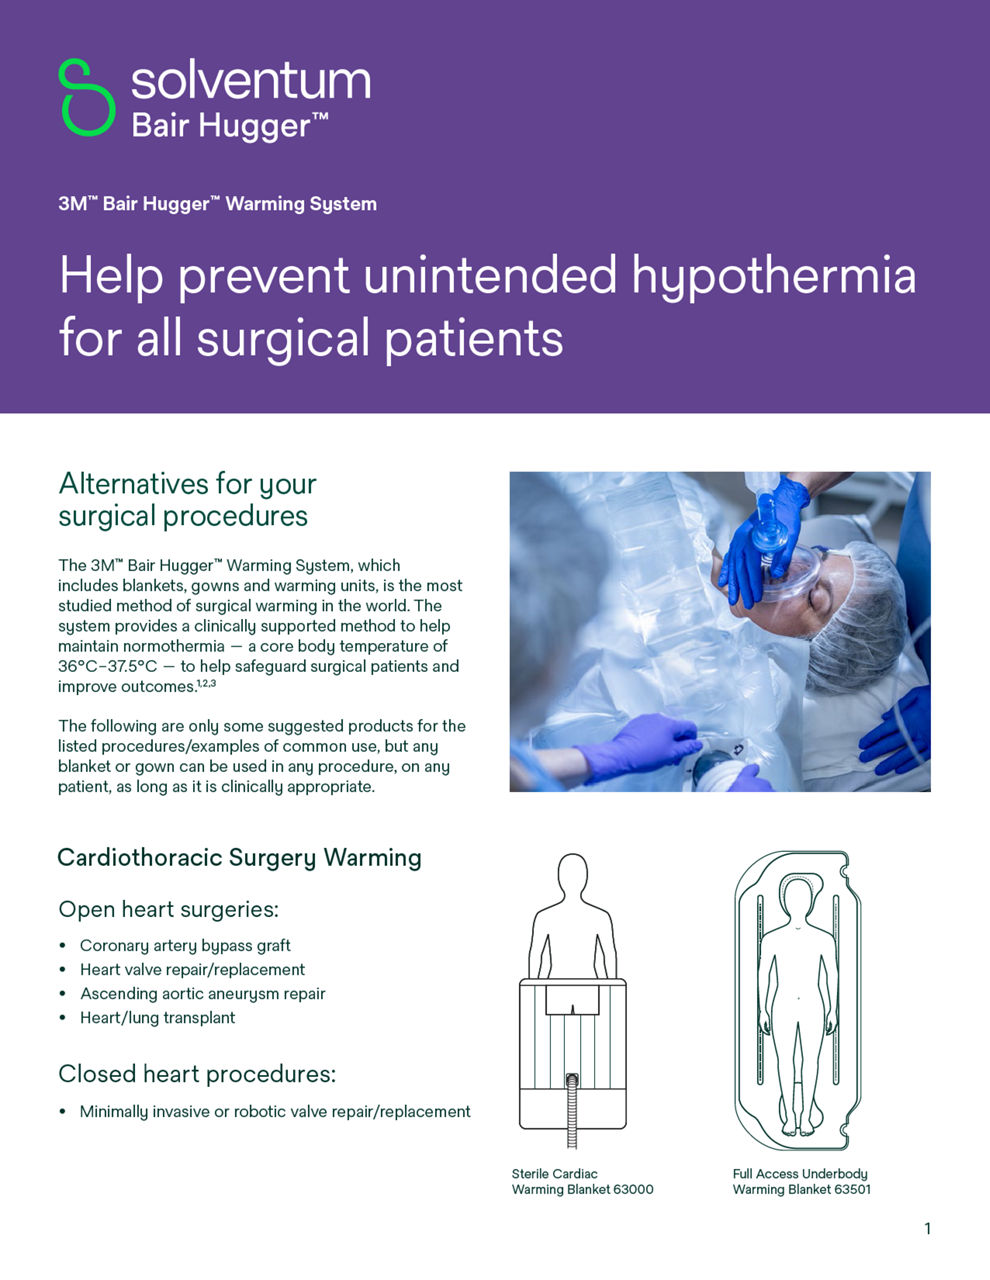
Bair Hugger Temperature Management Solutions provide an integrated approach to patient warming and temperature monitoring. Designed to work in harmony, each component supports consistent temperature management, real-time visibility, and adaptability across the perioperative journey.


NOTE: Specific indications, limitations, contraindications, warnings, precautions and safety information exist for these products and therapies. Please consult a clinician and product instructions for use prior to application. Rx only.
Start and end your patients’ perioperative journey with our 3M Bair Hugger Temperature Management System
By maintaining a normothermic core body temperature a patient's length of stay can be reduced by 2.6 days.11
How to proactively manage normothermia throughout the perioperative journey:
Actively measure your patients’ temperature. Prewarm them with the 3Mᵀᴹ Bair Huggerᵀᴹ Warming System to help prevent hypothermia.
Preoperative (pre-op)


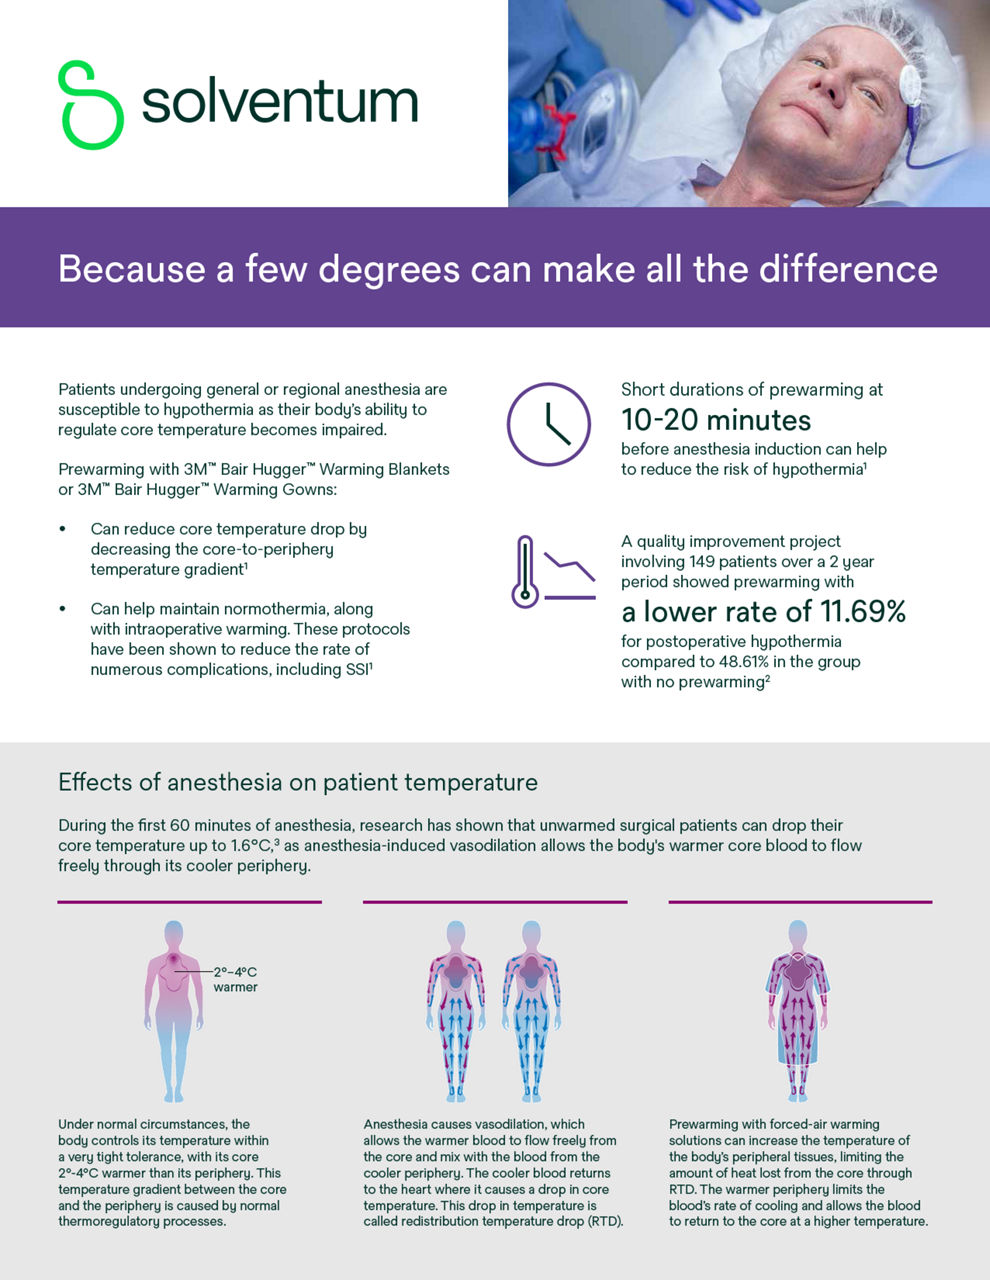
Prewarming prior to the induction of anesthesia helps to maintain normothermia and mitigate the effects of heat redistribution caused by anesthesia.
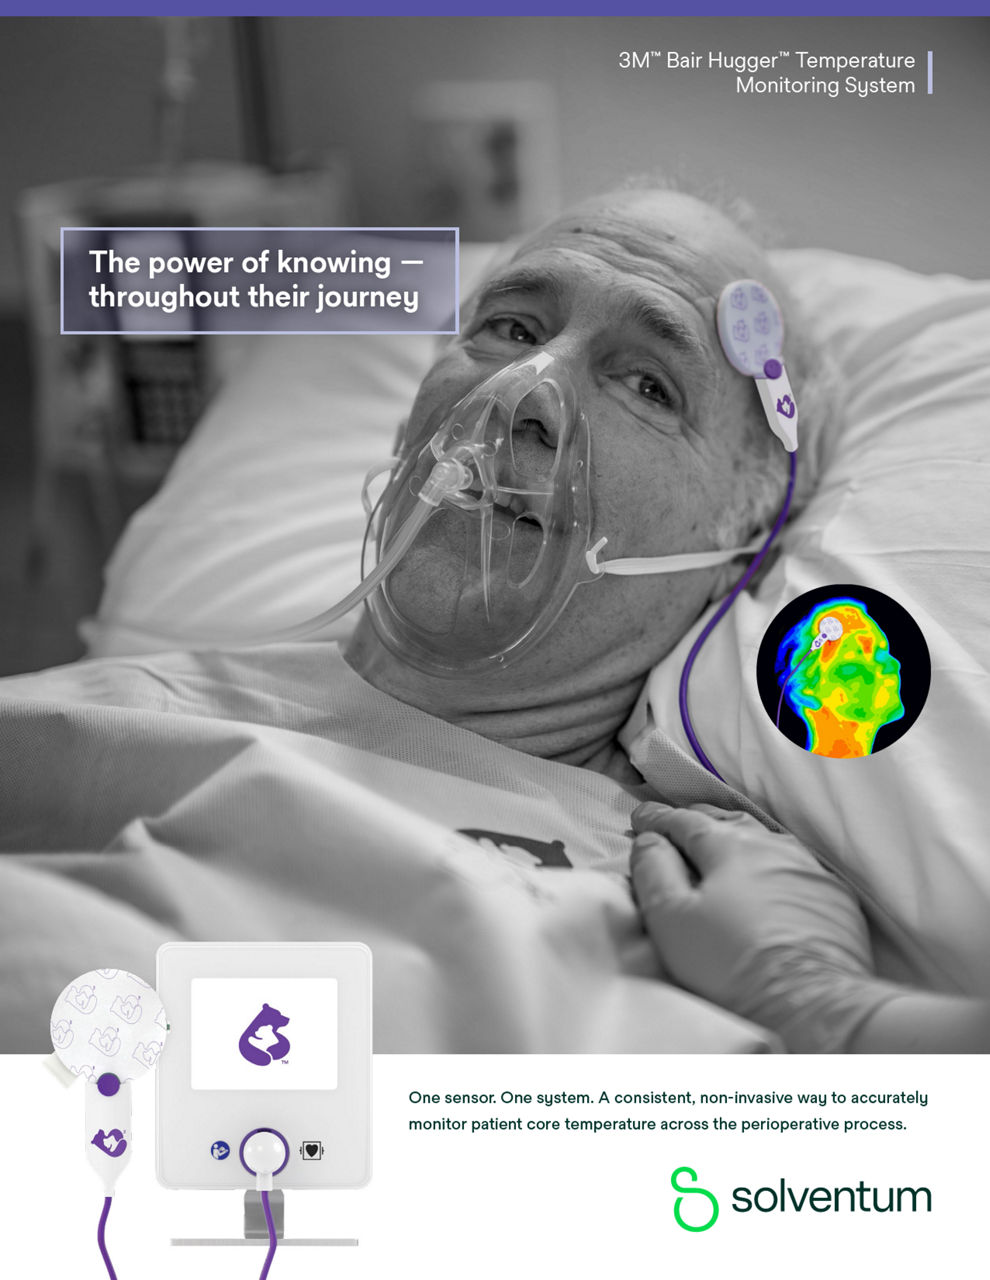
Monitor your patients’ core body temperature during surgery with the 3Mᵀᴹ Bair Huggerᵀᴹ Temperature Monitoring System. Proactively help achieve and maintain normothermia with 3Mᵀᴹ Bair Huggerᵀᴹ Warming System.
Intraoperative (intra-op)

Continue to monitor your patients’ temperature. Warm them with our 3Mᵀᴹ Bair Huggerᵀᴹ Warming System to help protect patients from unintended perioperative hypothermia.
Postoperative (post-op)
By maintaining a patient’s core body temperature near 36.5°C (36.6 + or - 0.5°C), patient length of stay has been shown to be reduced by 2.6 days.21

Resources to help maintain normothermia
The temperature monitoring process can be overwhelming. We offer useful resources to help you learn more about our solutions and how they can help you monitor and maintain your patients’ normal core body temperature — normothermia — throughout their perioperative journey.







References:
- Kurz A, Sessler DI, Lenhardt R. Perioperative normothermia to reduce the incidence of surgical-wound infection and shorten hospitalization. Study of Wound Infection and Temperature Group. N Engl J Med. 1996;334(19):1209-1215.
- Kurz A, Sessler DI, Lenhardt R. Perioperative normothermia to reduce the incidence of surgical-wound infection and shorten hospitalization. Study of Wound Infection and Temperature Group. N Engl J Med. 1996;334(19):1209-1215.
- Bush HL Jr, Hydo LJ, et al. Hypothermia during elective abdominal aortic aneurysm repair: the high price of avoidable morbidity. J Vasc Surg. 1995;21:392-400; discussion 400-392.
- Lau A, Lowlaavar N, Cooke EM, et al. Effect of preoperative warming on intraoperative hypothermia: a randomized-controlled trial. Can J Anesth. 2018. doi.org/10.1007/s12630-018-1161-8.
- Kurz A, Sessler DI, Lenhardt R. Perioperative normothermia to reduce the incidence of surgical-wound infection and shorten hospitalization. NEJM. 1996 May 9; 334 (19): 1209-16.
- Horn, EP, Bein B, Bohm R, Steinfath M, Sahilin, and Hocker J. The effect of short time periods of pre-operative warming in the prevention of peri-operative hypothermia. Anaesthesia. 2012; 67: 612–617.
- Nelson G, Altman AD, Nick A, et al. Guidelines for pre- and intra-operative care in gynecologic/oncology surgery: Enhanced Recovery After Surgery (ERAS®) Society recommendations — Part I. Gynecologic Oncology. 2015; 2016; 140: 313-322.
- National Institute for Health and Care Excellence. Hypothermia: prevention and management in adults having surgery. Clinical Guideline [CG65]. (2016). https://www.nice.org.uk/guidance/cg65/chapter/Recommendations#perioperative-care. Published April 2008. Updated December 2016. Accessed July 18, 2019.
- Forstot RM. The etiology and management of inadvertent perioperative hypothermia. J Clin Anesth. 1995;7:657-674.
- Leslie K, Sessler DI. Perioperative hypothermia in the high-risk surgical patient. Best Pract Res Clin Anaesthesiol. 2003;17:485-498.
- Mahoney CB, Odom J. Maintaining intra-operative normothermia: a meta-analysis of outcomes with costs. AANA J. 1999;67(2):155-163.
- Schroeck H, Lyden AK, Benedict WL, Ramachandran SK. Time Trends and Predictors of Abnormal Postoperative Body Temperature in Infants Transported to the Intensive Care Unit. Anesthesiology Research and practice. 2016:7318137.
- Hooper VD, Chard R, Clifford T, Fetzer S, Fossum S, Godden B, Martinez EA, Noble KA, O’Brien D, Odom-Forren J, Peterson C, Ross J, Wilson L. ASPAN’s Evidence-Based Clinical Practice Guideline for the Promotion of Perioperative Normothermia: Second Edition. J PeriAnesth Nurs. Vol 25, No 6 (December), 2010: pp 346-365.
- 3M Data on File: EM-05-297733, EM-05-711315.
- 3M™ Bair Hugger™ System Research Compendium, 2017 at: FAWFACTS.com.
- 3M Data on File: EM-05-233213, EM-05-268428.
- U.S. News & World Report. Best Hospitals 2025-2026 Honor Roll. Published July 29, 2025. U.S. News Best Hospitals.
- Horn, EP, Bein B, Bohm R, Steinfath M, Sahilin, and Hocker J. The effect of short time periods of pre-operative warming in the prevention of peri-operative hypothermia. Anaesthesia. 2012; 67: 612–617.
- Lau A, Lowlaavar N, Cooke EM, et al. Effect of preoperative warming on intraoperative hypothermia: a randomized-controlled trial. Can J Anesth. 2018. doi.org/10.1007/s12630-018-1161-8.
- National Institute for Health and Care Excellence. Hypothermia: prevention and management in adults having surgery. Clinical Guideline [CG65]. (2016). https://www.nice.org.uk/guidance/cg65/chapter/Recommendations#perioperative-care. Published April 2008. Updated December 2016. Accessed July 18, 2019.
- Kurz A, Sessler DI, Lenhardt R. Perioperative normothermia to reduce the incidence of surgical-wound infection and shorten hospitalization. NEJM. 1996 May 9; 334 (19): 1209-16.
- Horowitz PE, Delagarza MA, Pulaski JJ, Smith RA. Flow rates and warming efficacy with Hotline and Ranger blood/fluid warmers. Anesth Analg. 2004; 99 (3): 788-792.
- Nelson G, Altman AD, Nick A, et al. Guidelines for pre- and intra-operative care in gynecologic/oncology surgery: Enhanced Recovery After Surgery (ERAS®) Society recommendations — Part I. Gynecologic Oncology. 2015; 2016; 140: 313-322.
- Frank SM, Fleisher LA, Breslow MJ, et al. Perioperative maintenance of normothermia reduces the incidence of morbid cardiac events. A randomized clinical trial. JAMA. 1997; 277 (14): 1127-1134.
- Scott AV, Stonemetz JL, Wasey JO, Johnson DJ, Rivers RJ, Koch CG, et al. (2015) Compliance with Surgical Care Improvement Project for Body Temperature Management (SCIP Inf-10) Is Associated with Improved Clinical Outcomes. Anesthesiology. 123: 116–125.
- Anderson DJ. Strategies to prevent surgical site infections in acute care hospitals: 2014 update. Infection Control and Hospital Epidemiology. 2014; 35 (6): 605–627. doi: 10.1086/676022. Accessed December 15, 2016.
- Melling AC, Ali B, Scott EM, Leaper DJ. Effects of preoperative warming on the incidence of wound infection after a clean surgery: a randomized controlled trial. Lancet. 2001; 358 (9285): 876-880.
- Van Duren A. Patient Warming Plays a Significant Role in Satisfaction, Clinical Outcomes. Infection Control Today. 2008; 12 (6): 1-4 (reprint page numbers).
- Rajagopalan S, et al. The Effects of Mild Perioperative Hypothermia on Blood Loss and Transfusion Requirement. Anesthesiology. 2008; 108: 71-7.
- Bräuer, A., English, M. J., Sander, H., Timmermann, A., Braun, U., & Weyland, W. (2002). Construction and evaluation of a manikin for perioperative heat exchange. Acta Anaesthesiologica Scandinavica,46, 43-50. doi:10.1034/j.1399- 6576.2002.460108.x 8. 7.
- Bräuer, A., English, M. J., Steinmetz, N., Lorenz, N., Perl, T., Braun, U.,& Weyland, W. (2002). Comparison of forced-air warming systems with upper body blankets using a copper manikin of the human body. Acta Anaesthesiologica Scandinavica, 46, 965-972. doi:10.1034/j.1399-6576.2002.460807.x 9.
- Bräuer, A., English, M. J., Lorenz, N., Steinmetz, N., Perl, T., Braun, U.,& Weyland,W. (2003). Comparison of forced-air warming systems with lower body blanketsusing a copper manikin of the human body. Acta Anaesthesiologica Scandinavica,2003, 58-64. doi:10.1034/j.1399-6576.2003.470110.x